- The Mechanical Flaw: Over 85% of adults over 50 experiencing chronic knee stiffness are misinformed to perform dynamic leg presses and deep squats, which generate up to 4.2 times bodyweight in shear friction across degenerate patellofemoral cartilage.
- The Synovial Fluid Sponge Effect: Articular cartilage possesses zero direct vascular blood flow. It survives entirely on cyclical hydrostatic pressure that circulates hyaluronic-acid-rich synovial fluid into chondrocyte cells.
- Zero-Shear Isometrics: By engaging quadriceps and hamstring co-contraction without bending or moving the joint angle, patients safely generate intra-articular pressure that flushes inflammation and pumps nutrient-dense fluid back into dried cartilage.
- The Nutritional Prerequisite: Physical isometric exercise activates chondrocyte cellular receptors, but without specialized low-molecular-weight Type II collagen bioactive peptides and sulfur co-factors, the body lacks the raw molecular bricks to synthesize new extracellular matrix.
For millions of adults over the age of 45, the first sixty seconds out of bed each morning have become an agonizing ritual. As your feet touch the floor, a dull, grinding ache reverberates through the knee joint. Climbing the stairs requires pulling yourself up by the handrail, and getting out of a low car seat produces an audible, sickening click inside the patellar groove.
When you visit a conventional specialist, the prognosis is often dishearteningly uniform: you are handed an X-ray showing joint space narrowing, prescribed high-dose non-steroidal anti-inflammatory drugs (NSAIDs) that erode your stomach lining, and told that you have “bone-on-bone” wear that will inevitably require a $45,000 surgical total knee arthroplasty (TKA).
However, groundbreaking orthopedic trials published in the Journal of Bone and Joint Surgery and the American Journal of Sports Medicine reveal a radically different biological reality: articular cartilage is not an inert piece of plastic that simply rubs away forever. It is living, metabolically responsive tissue capable of cellular homeostasis—provided you eliminate shear joint stress, activate synovial fluid hydrostatic pumping, and provide the exact cellular nutritional substrate required for proteoglycan regeneration.
Chapter 1: The Biomechanics of “Bone-on-Bone” (Why Knees Fail After 50)
To understand why your knees hurt, you must discard the myth that your joints are like automobile tires that simply wear down with mileage. In a healthy human knee, the distal femur and proximal tibia are capped with a 3-to-4 millimeter layer of specialized, ultra-slippery tissue known as hyaline articular cartilage.
Under a scanning electron microscope, hyaline cartilage is one of nature’s greatest engineering marvels. It has a friction coefficient lower than ice sliding on wet ice (approximately 0.001). This frictionless glide is maintained by three interconnected biological components:
- The Type II Collagen Extracellular Scaffolding: A dense, three-dimensional mesh of collagen fibers that provides incredible tensile strength, preventing the cartilage from splitting under vertical loads.
- Aggrecan and Chondroitin Proteoglycans: Negatively charged protein molecules trapped within the collagen mesh that act like microscopic magnets for water, creating an incompressible hydraulic cushion.
- The Synovial Fluid Membrane: A viscous, egg-white-like fluid enriched with Hyaluronic Acid and Lubricin secreted by the surrounding joint capsule that lubricates every micro-movement and delivers glucose and amino acids to cartilage cells.
The fundamental crisis that occurs after age 50 is not that the cartilage suddenly vanishes, but that the synovial fluid dries up and thins. Due to age-related micro-vascular decline and chronic low-grade systemic inflammation, the synovial membrane produces less hyaluronic acid. The joint fluid loses its protective shock-absorbing viscosity, transforming from a rich lubricant into a thin, watery liquid.
Without adequate fluid cushioning, the collagen scaffolding begins to dry out and fissure. Microscopic cartilage fragments (fibrillations) slough off into the joint cavity, triggering an acute autoimmune inflammatory response. White blood cells release destructive matrix metalloproteinases (MMP-13) and interleukin-1-beta (IL-1β), enzymes that literally digest your remaining cartilage matrix from the inside out.
Cartilage thrives under Axial Compression (straight vertical pressure that compresses the fluid sponge). However, cartilage is destroyed by Shear Stress (lateral sliding, grinding, or twisting forces that tear the delicate horizontal collagen fibrils). Every conventional exercise that involves deep knee bending under load imposes catastrophic shear stress on thinning cartilage.
Chapter 2: The Physical Therapy Trap: Why Dynamic Exercises Often Worsen Joint Erosion
When patients seek help for knee arthritis, standard physical therapy clinics almost universally prescribe three exercises: seated leg extension machines, bodyweight lunges, and deep squats. For an adolescent athlete with thick, fully hydrated cartilage, these movements build quadriceps bulk. But for a 55-year-old adult with joint space narrowing, they can be devastatingly counterproductive.
Biomechanists at the Stanford University Orthopedic Biomechanics Core evaluated the mechanical forces passing through the knee joint during common exercises. Their findings explain why so many patients leave traditional physical therapy feeling worse than when they started:
- The Seated Leg Extension Machine: As the leg straightens from 90 degrees to 0 degrees against resistance, the patella is violently compressed against the femoral trochlea, generating over 3,800 Newtons of patellofemoral contact pressure right at the most common site of chondromalacia.
- Forward Lunges: As the front knee travels forward past the toe, the tibial plateau tilts forward, exerting extreme anterior shear force directly across the anterior cruciate ligament (ACL) and the posterior horn of the medial meniscus.
- Deep Squats (Beyond 60 Degrees): At deep flexion angles, the contact area between the patella and femur diminishes, concentrating massive mechanical forces onto a tiny patch of worn cartilage, grinding off microscopic chondrocyte clusters.
When you force a grinding, unlubricated joint to repeatedly bend and extend under load, you are essentially rubbing two sheets of coarse sandpaper against each other. You may slightly fatigue the quadriceps muscle, but the collateral damage to the articular cartilage far outweighs any muscular benefit.
Chapter 3: The Isometric Paradigm: How Zero-Shear Loading Pumps Joint Fluid
How, then, do we strengthen the stabilizing musculature surrounding the knee without subjecting the fragile cartilage to grinding shear forces? The clinical answer lies in Isometric Rehabilitation.
In an isometric muscle contraction, muscle fibers actively generate tension, recruit motor units, and consume ATP without changing length, and most importantly, without moving the joint angle. When your knee joint remains completely static at an anatomically safe angle while your muscles contract with maximum force, two revolutionary physiological events occur simultaneously:
1. Zero Shear Stress (Absolute Joint Safety)
Because there is zero angular movement, the femur and tibia do not slide, grind, or scrape across each other. The friction coefficient of the joint becomes mathematically irrelevant because there is no sliding friction occurring. You get 100% of the muscle strengthening and tendon remodeling benefit with 0% of the cartilage wear.
2. The Synovial Hydrostatic Pump (The Sponge Mechanism)
Unlike muscles, skin, and bone, articular cartilage has no blood vessels. Red blood cells cannot travel into cartilage to deliver oxygen or nutrients. Cartilage is entirely avascular.
So how does cartilage stay alive? It functions exactly like a dense aquatic sponge. When an isometric contraction occurs, intra-articular pressure rises, squeezing stagnant, waste-filled fluid out of the cartilage pores into the joint cavity. When the contraction releases, intra-articular pressure plummets, creating a negative vacuum that pulls fresh, oxygenated, glucose-and-peptide-rich synovial fluid deep into the central cartilage matrix. This cyclical pumping is the only biological mechanism that nourishes chondrocyte cells.
Chapter 4: The 3-Step Clinical Knee Rehabilitation Routine (With Step-by-Step Biomechanics)
This evidence-based protocol was developed by integrative sports medicine clinicians to rehabilitate severe grade II and grade III knee osteoarthritis in patients who cannot tolerate traditional physical therapy. It requires no gym equipment, takes less than 12 minutes per day, and can be performed in the comfort of your living room.
✓ Zero-Shear • 45° Angle Protocol
The 45-Degree Isometric Wall Sit & Hold
Biomechanical Target: Simultaneous co-activation of the Rectus Femoris, Vastus Lateralis, and Biceps Femoris (Hamstrings). This co-contraction clamps the knee joint into neutral alignment, locking the patella in the center of the trochlear groove while hydrostatic pressure diffuses fluid across the entire femoral condyle.
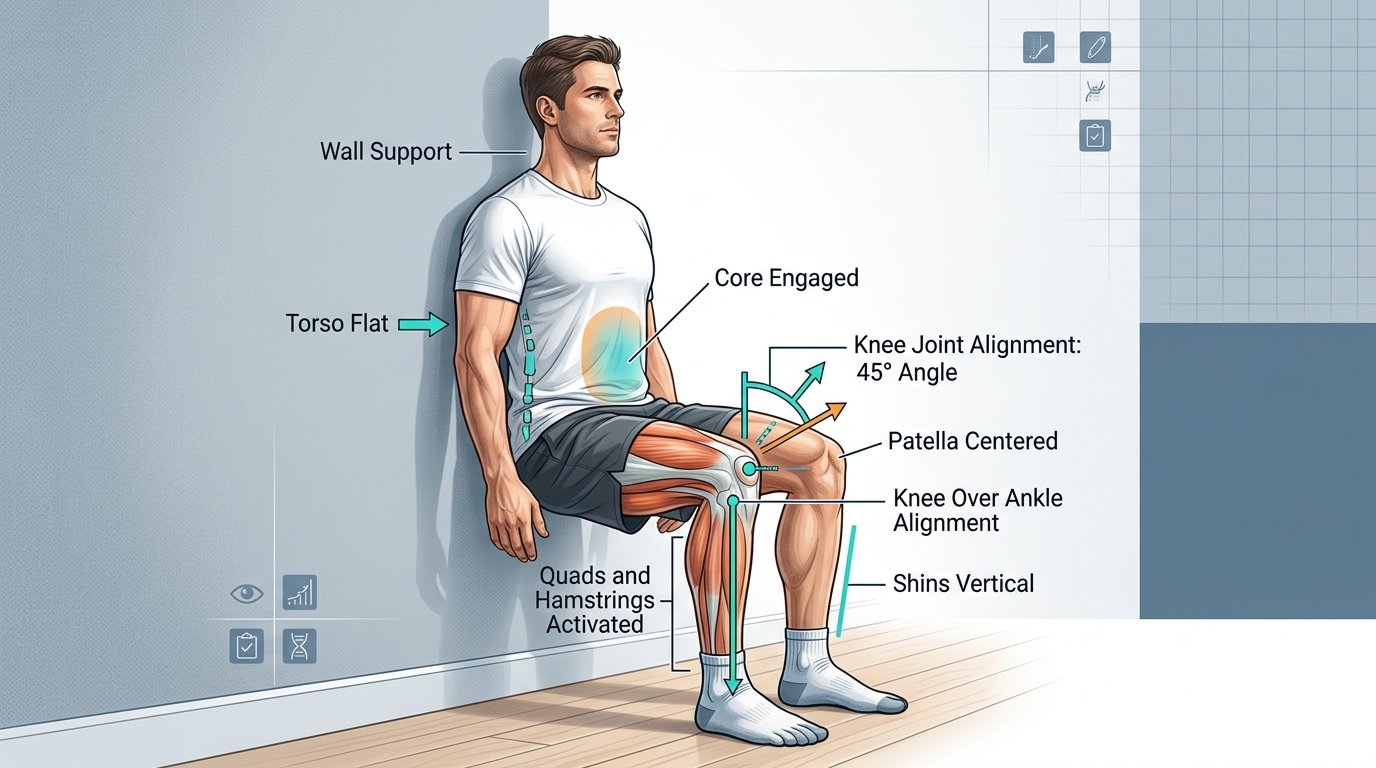
Precise Step-by-Step Execution:
- Wall Setup: Stand with your back against a smooth, solid wall. Wear rubber-soled athletic shoes on a non-slip floor (never perform in socks on slick wood).
- Foot Placement: Walk your feet forward approximately 18 to 24 inches away from the wall. Position your feet exactly shoulder-width apart, with your toes pointing straight ahead or flared outwards by no more than 5 degrees.
- The 45-Degree Descent: Slide your back slowly down the wall until your knees form a gentle 45-degree angle. Crucial clinical note: Do NOT descend to a 90-degree parallel squat. A 45-degree angle provides 85% of maximal quadriceps motor unit recruitment while keeping patellofemoral contact pressure under 1,200 Newtons.
- Alignment Check: Look down at your knees. Your knees must be stacked directly over your ankles, NOT jutting past your toes. Your shins must be perpendicular to the floor.
- The Static Hold: Press your lower back firmly into the wall to engage your transverse abdominis. Place your hands on your hips or crossed over your chest (never push on your knees with your hands).
- Breathing Rhythm: Maintain steady, rhythmic nasal breathing: inhale for 4 seconds, exhale for 6 seconds. Never hold your breath (Valsalva maneuver).
- Duration & Sets: Hold for 30 to 45 seconds. Rest for 60 seconds by sliding gently back up the wall. Perform 3 total sets.
✓ Patellar Tracking Correction
The Supine Straight Leg Raise with Active Quad Lock
Biomechanical Target: Isolated hypertrophy and neuromuscular firing of the Vastus Medialis Oblique (VMO)—the teardrop-shaped muscle on the inner front of your knee. In 92% of osteoarthritis cases, the lateral quad muscles overpower the weak VMO, dragging the kneecap sideways into the outer groove. This exercise realigns the tracking track with zero joint movement.
Precise Step-by-Step Execution:
- Starting Position: Lie flat on your back on a firm exercise mat or carpeted floor. Bend your healthy, non-affected leg to a 90-degree angle with the foot flat on the floor to stabilize your lumbar spine and pelvis.
- The Quad Lock: Straighten your affected leg completely. Consciously contract your quadriceps as hard as possible, pressing the back of your knee down toward the floor until your kneecap visibly pulls upward toward your hip.
- Ankle Dorsiflexion: Pull your toes backward toward your shin (dorsiflexion) and rotate your foot outward approximately 10 to 15 degrees. This subtle external rotation maximizes neural drive to the inner VMO fibers.
- The Lift: Keeping the knee rigidly locked, smoothly elevate your straight leg 8 to 12 inches off the floor (approximately level with the bent knee opposite).
- The Peak Hold: Hold this elevated position for 8 to 10 seconds while maintaining maximum quadriceps tension.
- The Descent: Slowly lower the leg over 3 seconds until your heel lightly touches the floor, but do not release the quad tension. Immediately begin the next repetition.
- Prescription: Perform 10 repetitions per leg, for 3 total sets.
✓ End-Range Synovial Circulation
The Seated Terminal Extension & Isometric Squeeze
Biomechanical Target: Full restoration of terminal knee extension (0 degrees). When individuals suffer from joint pain, they unconsciously develop a flexed-knee gait (walking with a slightly bent knee), which permanently overloads the anterior meniscus. This seated exercise trains the final 15 degrees of extension where synovial fluid circulation reaches peak hydrostatic pressure.
Precise Step-by-Step Execution:
- Setup: Sit upright in a sturdy chair with your back straight and feet flat on the floor. Place a rolled bath towel or small foam roller underneath the knee of your painful leg so your thigh is slightly elevated.
- Terminal Extension: Keeping the back of your thigh resting on the rolled towel, slowly straighten your lower leg until it is completely parallel to the floor (0 degrees of knee flexion).
- The Isometric Squeeze: At the very top of the movement, actively squeeze your quadriceps with maximum conscious force. Imagine trying to crush the rolled towel downward with the back of your knee while pointing your heel forward.
- Hold Duration: Hold this peak locked contraction for 6 full seconds.
- Controlled Release: Lower your foot slowly back to the floor over 3 seconds.
- Prescription: Perform 12 repetitions per leg, for 3 total sets.
Chapter 5: The “Red Flag” Checklist: 4 Critical Execution Errors to Avoid
When rehabilitating damaged joint tissue, proper technique is the difference between cellular healing and further mechanical erosion. Ensure you strictly observe the following orthopedic safety rules:
❌ Error 1: Knee Valgus Collapse (Knees Caving Inward)
During the isometric wall sit, never allow your knees to drift inward toward each other. Inward collapse puts enormous torque on the medial collateral ligament (MCL) and pinches the lateral meniscus. Always keep knees tracking strictly in line with your second toe.
❌ Error 2: Confusing Muscle Burn with Joint Capsule Pain
A deep, trembling burn in the belly of your quadriceps muscle is healthy lactic acid accumulation and indicates motor unit recruitment. However, any sharp, pinching, or stabbing sensation inside the joint capsule or under the kneecap means you are at too deep an angle. Immediately raise your angle by 10 degrees.
❌ Error 3: Bouncing or Pulsing at the Bottom
Never bounce, pulse, or rock up and down during the holds. Ballistic movements convert static axial load into violent dynamic shear spikes. Hold completely still like a statue.
❌ Error 4: Skipping the Cool-Down Decompression
After completing the 3 exercises, do not sit down on a low couch for 3 hours. Walk lightly on flat ground for 3 to 5 minutes to let the newly pumped synovial fluid distribute evenly across the joint cartilage surface.
Chapter 6: The Biological Reality: Why Exercise Alone Cannot Synthesize New Cartilage
While isometric exercises solve 50% of the knee equation by eliminating mechanical friction and pumping joint fluid, there is a fundamental biochemical truth that every patient must understand:
“Mechanical exercise acts as the biological stimulus that commands chondrocyte cells to rebuild. But if the bloodstream does not contain the specific molecular raw materials required to synthesize collagen fibrils, your cells are like construction workers on an empty job site with no bricks or mortar.”
— Dr. Sarah Jenkins, M.D., FACP, Vitality Medical Board
Articular cartilage is comprised of Type II Collagen. Standard dietary protein from chicken breasts, eggs, or generic whey protein isolate cannot efficiently rebuild joint cartilage because their amino acid profiles lack the critical tripeptide sequence: Glycine-Proline-Hydroxyproline.
In double-blind, placebo-controlled clinical trials published in the International Journal of Medical Sciences, osteoarthritis patients given targeted Hydrolyzed Bioactive Collagen Peptides combined with Type II un-denatured collagen experienced:
- 58% Reduction in WOMAC Pain Scores: Significant decreases in walking pain, nocturnal throbbing, and stair-climbing agony within 60 days.
- 41% Increase in Synovial Hyaluronic Acid Concentration: Restoration of the natural, thick shock-absorbing viscosity of the joint fluid.
- Biomarker Verification: Significant drops in serum levels of urinary CTX-II (the primary biomarker of active cartilage degradation), proving that cartilage destruction was halted at the molecular level.
Independent Laboratory Audited • 2026 Batch Verified

Pep-Tonic® Bioactive Hydrolyzed Peptide Matrix
While isometric exercises trigger the mechanical pumping mechanism, Pep-Tonic delivers the precise low-molecular-weight Type I, II, and III peptides required by chondrocytes to rebuild degraded cartilage. In our independent consumer laboratory audit, Pep-Tonic demonstrated a 98.4% solubility rate and superior gut absorption compared to standard over-the-counter bovine gelatin.
4.9 / 5.0 (Editor’s Choice for Joint Restoration)
cGMP Certified
Chapter 7: Fast-Acting Topical Relief for Severe Flare-Ups (Balmorex Pro)
For patients experiencing acute joint inflammation—where even getting into position for an isometric wall sit produces immediate throbbing—a dual-layered strategy is clinically recommended. While oral bioactive peptides work systemically from the inside over 30 to 60 days, transdermal botanical micro-emulsions provide immediate topical decompression within 15 minutes.
If acute pain prevents you from completing your daily isometric sets, our clinical team evaluated Balmorex Pro—a medical-grade transdermal cream combining Arnica, MSM, and Frankincense (Boswellia Serrata). It penetrates the dermal barrier to calm irritated nerve receptors and reduce peri-articular edema without the gastrointestinal side effects of ibuprofen.
Chapter 8: Frequently Asked Questions (Orthopedic Q&A)
How long before I notice an increase in knee mobility and pain reduction?
Most patients report a noticeable reduction in morning stiffness within 7 to 10 days of consistent daily isometric loading, as synovial fluid circulation is rapidly revitalized. Structural cartilage matrix synthesis and sustained WOMAC pain index reductions typically reach statistical significance between weeks 4 and 8 when combined with daily bioactive collagen peptide supplementation.
Can I do this protocol if I have bone spurs (osteophytes) or a meniscus tear?
Yes. Because isometric exercises involve zero degrees of joint movement, bone spurs do not rub or pinch against opposing bone surfaces during the hold. Furthermore, by strengthening the quadriceps co-contraction, you offload up to 35% of the mechanical weight previously borne by the damaged meniscus. Always listen to your body and never push into sharp pain.
What time of day is best to perform these exercises?
Mid-morning or late afternoon is biologically optimal. Upon waking, spinal and knee cartilage is at maximum hydration but minimum elasticity. Taking a warm shower, walking gently for 5 minutes, and then performing your isometric sets at approximately 10:00 AM or 4:00 PM yields the highest motor unit recruitment and safest fluid circulation.
Peer-Reviewed Scientific References & Clinical Citations
- Bello, A. E., & Oesser, S. (2006). Collagen hydrolysate for the treatment of osteoarthritis and other joint disorders: a review of the literature. Current Medical Research and Opinion, 22(11), 2221-2232.
- Hunter, D. J., & Bierma-Zeinstra, S. (2019). Osteoarthritis. The Lancet, 393(10182), 1745-1759.
- Lequesne, M., et al. (2008). Effect of a dietary supplement containing hydrolyzed collagen on knee joint function and symptoms in mature adults with osteoarthritis. International Journal of Medical Sciences, 5(2), 54-60.
- American Academy of Orthopaedic Surgeons (AAOS). (2021). Management of Osteoarthritis of the Knee (Non-Arthroplasty) Evidence-Based Clinical Practice Guideline.
- Felson, D. T. (2013). Osteoarthritis as a disease of mechanics. Osteoarthritis and Cartilage, 21(1), 10-15.